
Chapter 4 · Keeping up the CRT · Case 1
CRT-P in AF: two different pacing percentages
Patient and episode
Patient
- Octogenarian, VISIONIST X4 CRT-P implanted four and a half years earlier, quadripolar LV lead; DDD 60-150 bpm, BiV with LV offset 0 ms, mode switch (ATR) to DDI; remote transmission after about 4 days of new AF, with heart failure symptoms
The recording
Tap a number on the trace, or an entry in the list below
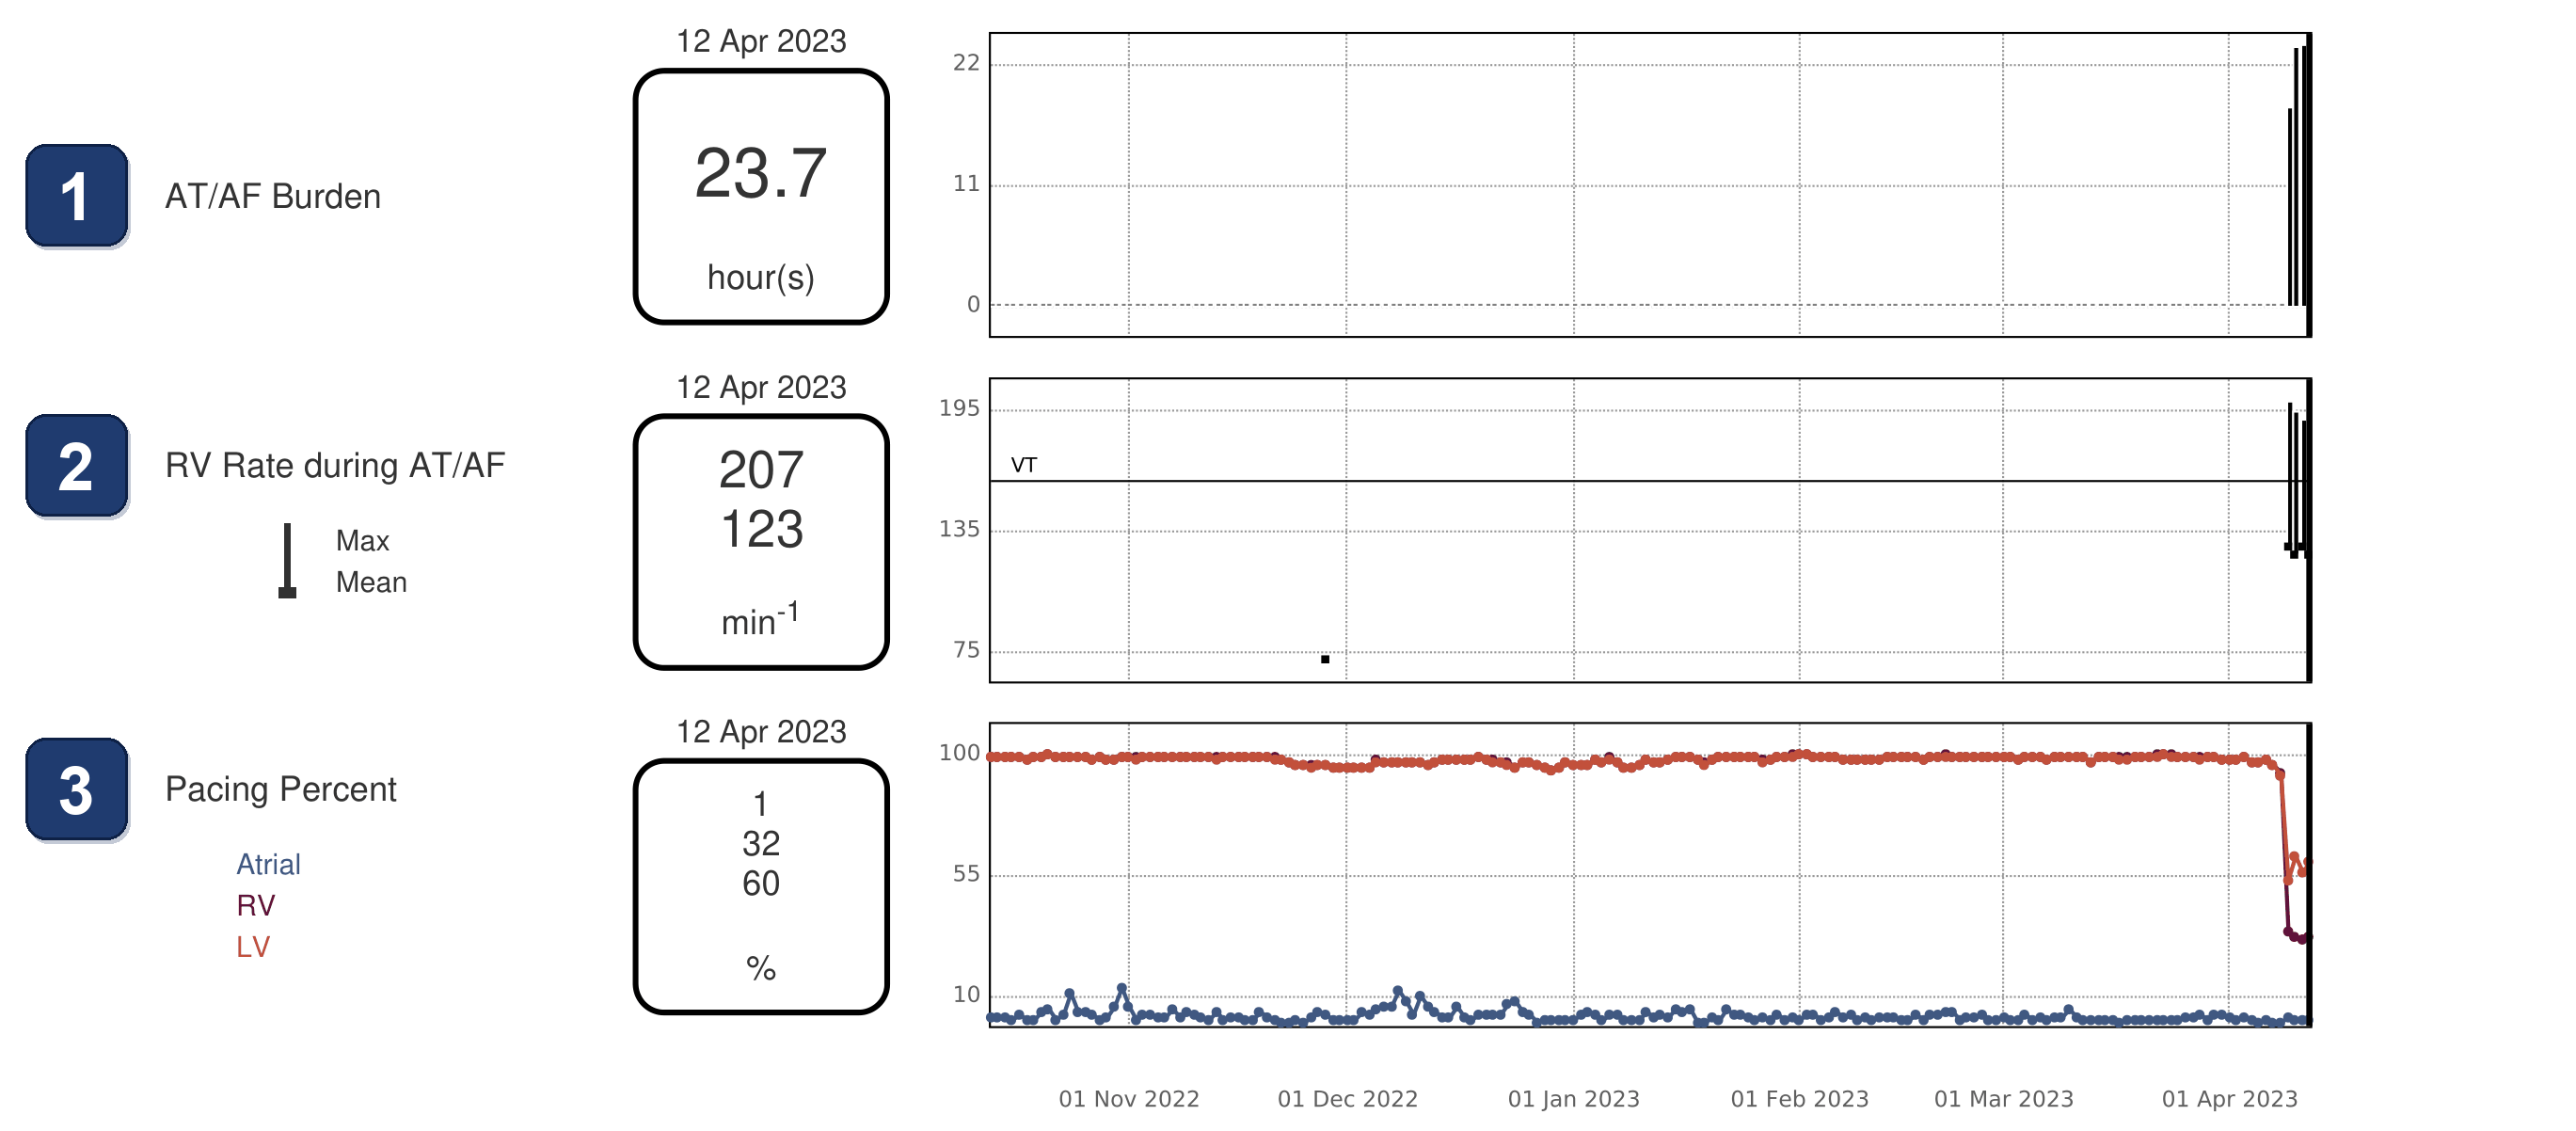

- Remote transmission, 6 months of trends: no AF until about 4 days before it, then AF almost all day (23.7 h the day before)
- Ventricular rate during the AF that day: mean 123 bpm, max 207 bpm. The AF is conducted fast
- Pacing: RV and LV about 95-100% for 6 months, then A 1%, RV 32%, LV 60% that same day: two different percentages. The counters since implant still read RV 99%, LV 99% (report p5): only the daily trend shows the drop
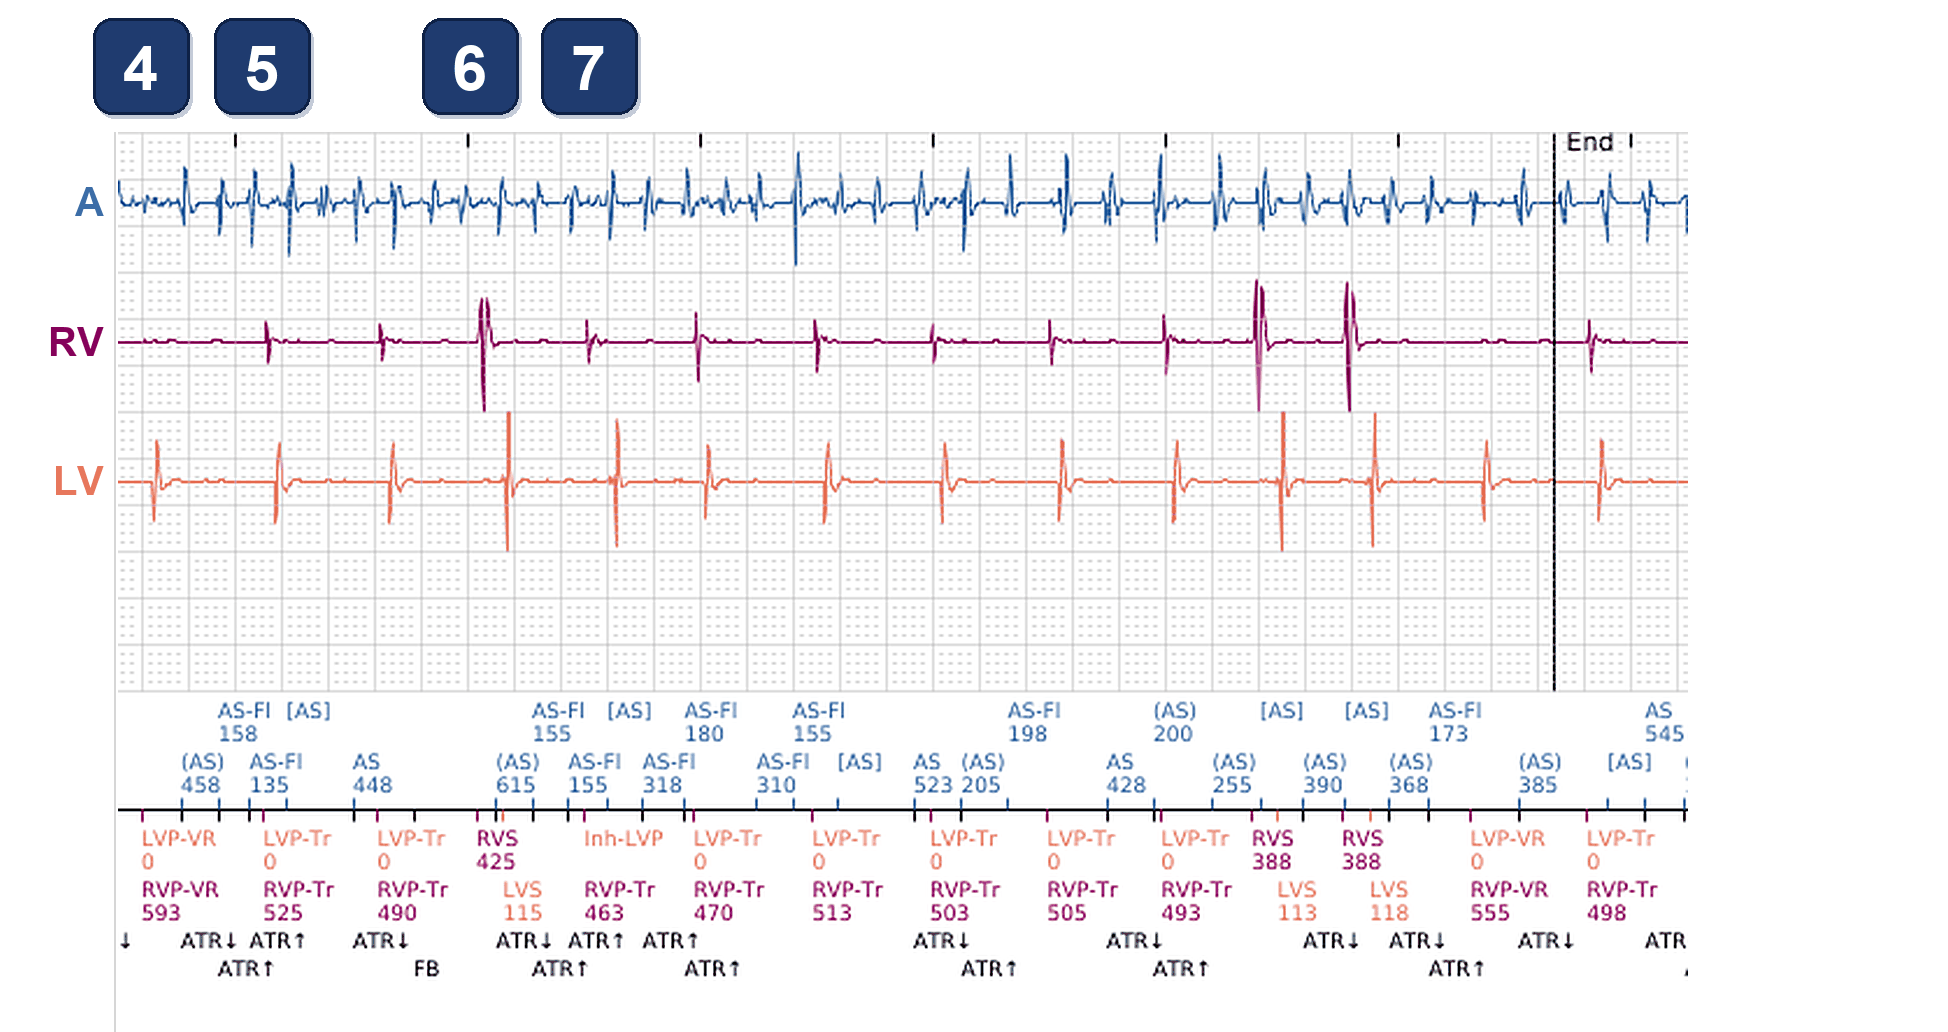
- Presenting EGM: AF on the A channel, no atrial sense is tracked (ATR mode switch, markers on the bottom line). With no conducted beat in time, VRR paces both ventricles together (LVP-VR 0, RVP-VR 593 ms): a true BiV beat, counted as RV paced and LV paced
- A conducted AF beat reaches the RV lead and is sensed there. The markers read LVP-Tr 0 and RVP-Tr 525 ms, but paradoxically the RV is not paced: the RV sense triggers the LV pace. The RV was already activated by the patient’s own beat, so the beat counts as RV sensed, LV paced: a missed beat for CRT
- RVS 425 ms (141 bpm), above the BiV Trigger maximum pacing rate (nominal 130 bpm): not triggered. The LV is activated 115 ms after the RV (LVS 115), with large native RV and LV EGMs: RVS-LVS, a missed beat
- 463 ms later the RV sense still shows RVP-Tr, but the LV pace is withheld (Inh-LVP): it would come 348 ms after the LV sense of the beat before, inside the LV protection period. No LV pacing and no real RV pacing: a missed beat, like an RVS-LVS beat
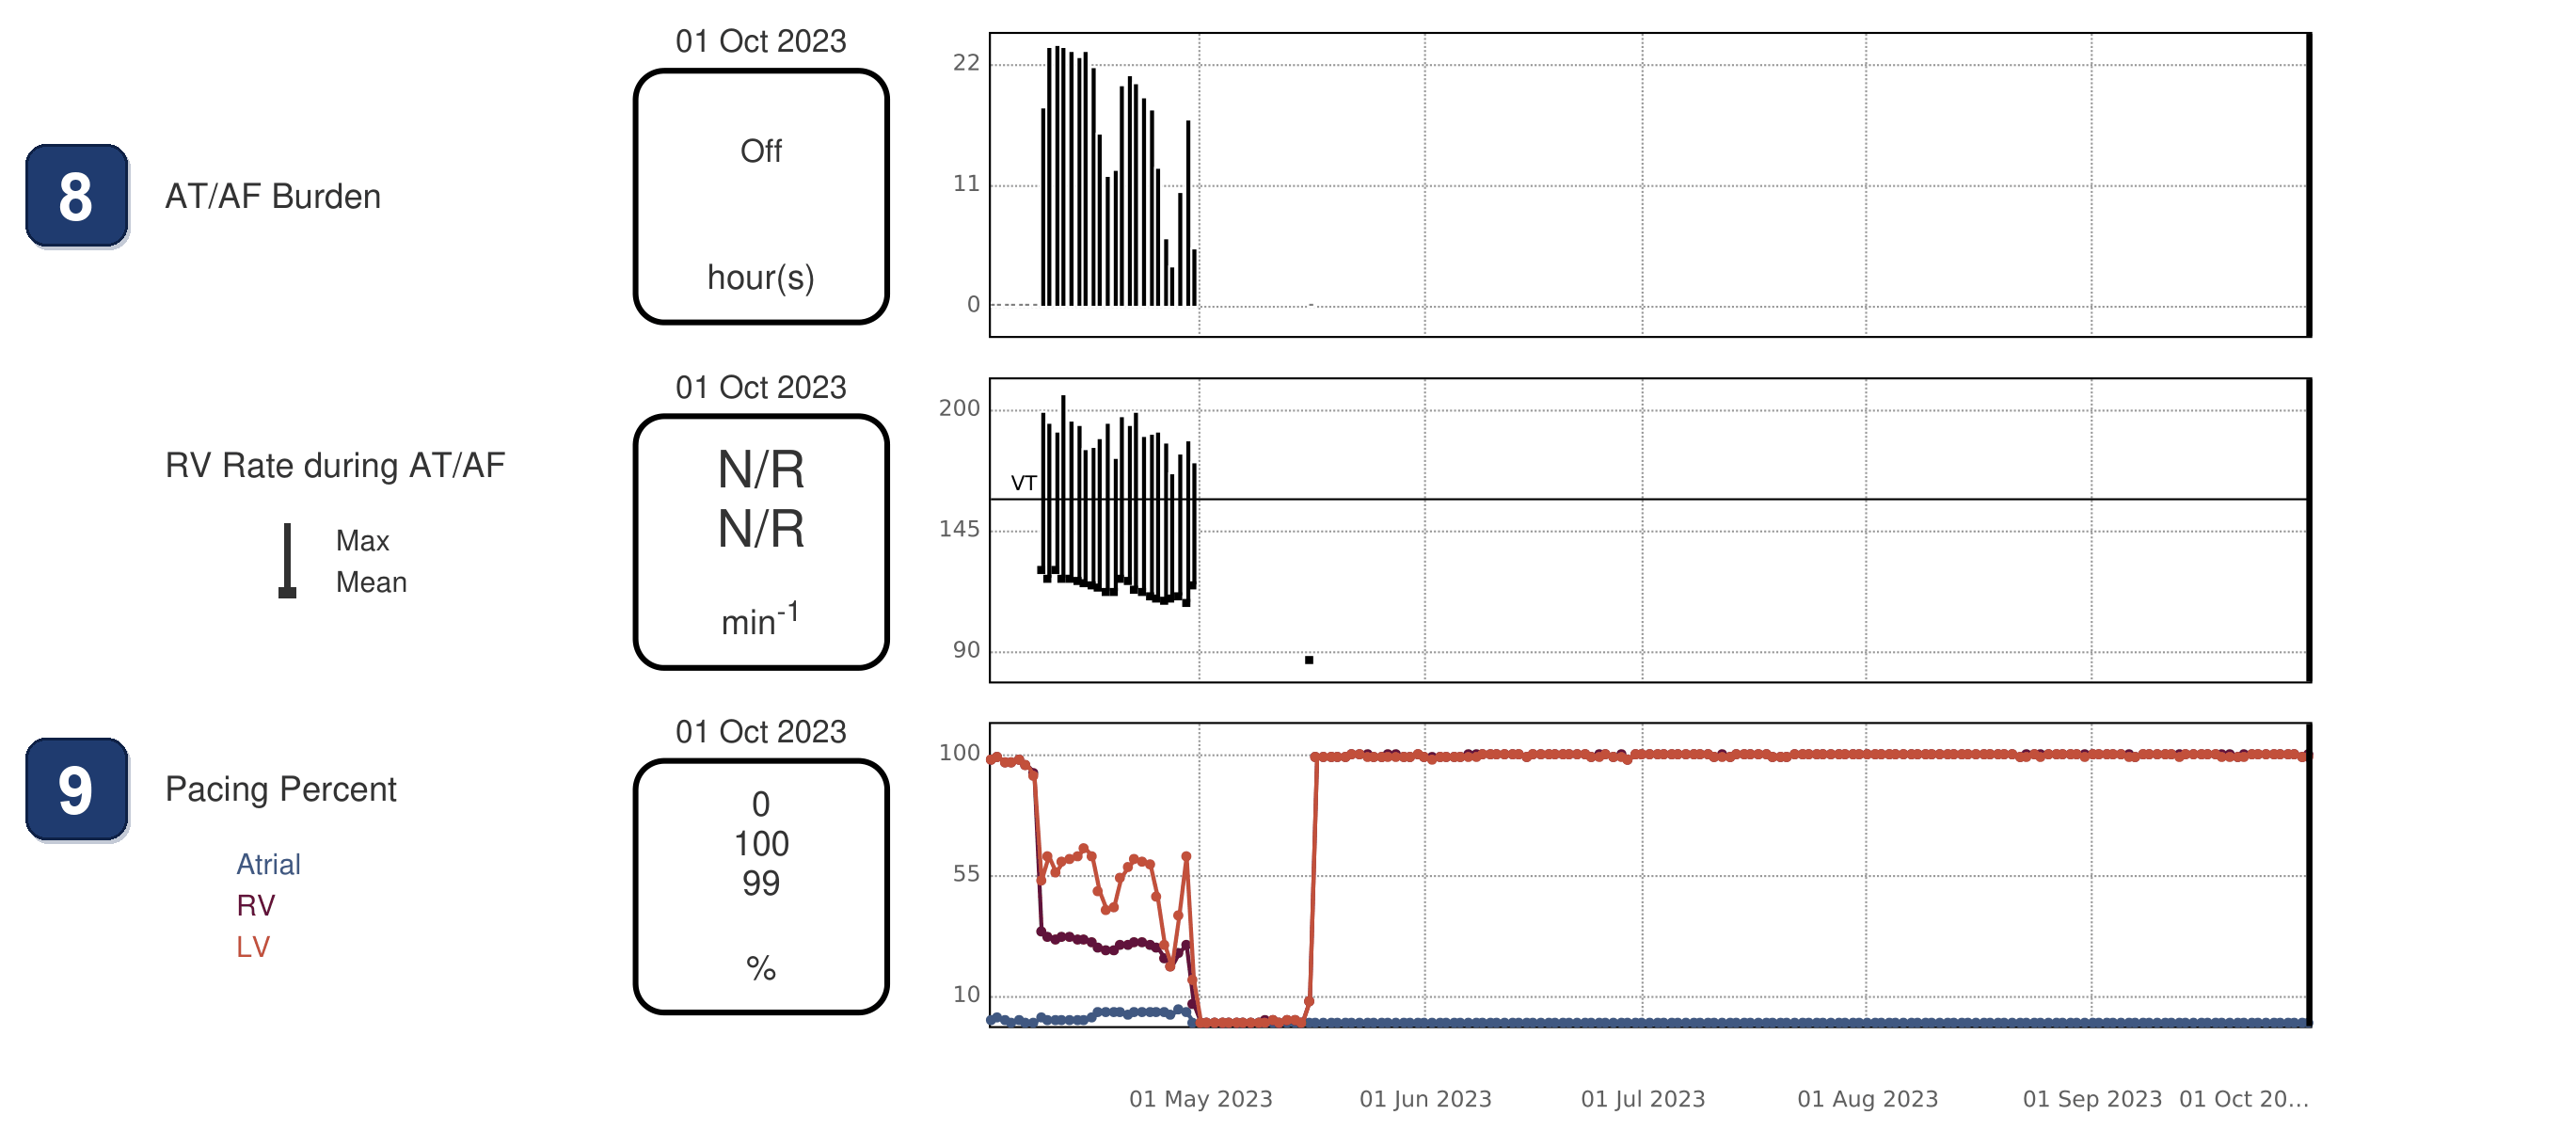
- Second report, nearly 6 months later: persistent AF, with RV rates up to about 200 bpm (row below). Then a His ablation is performed. Suddenly no more data, because of the mode change
- After the His ablation, RV 100% and LV 99% every day
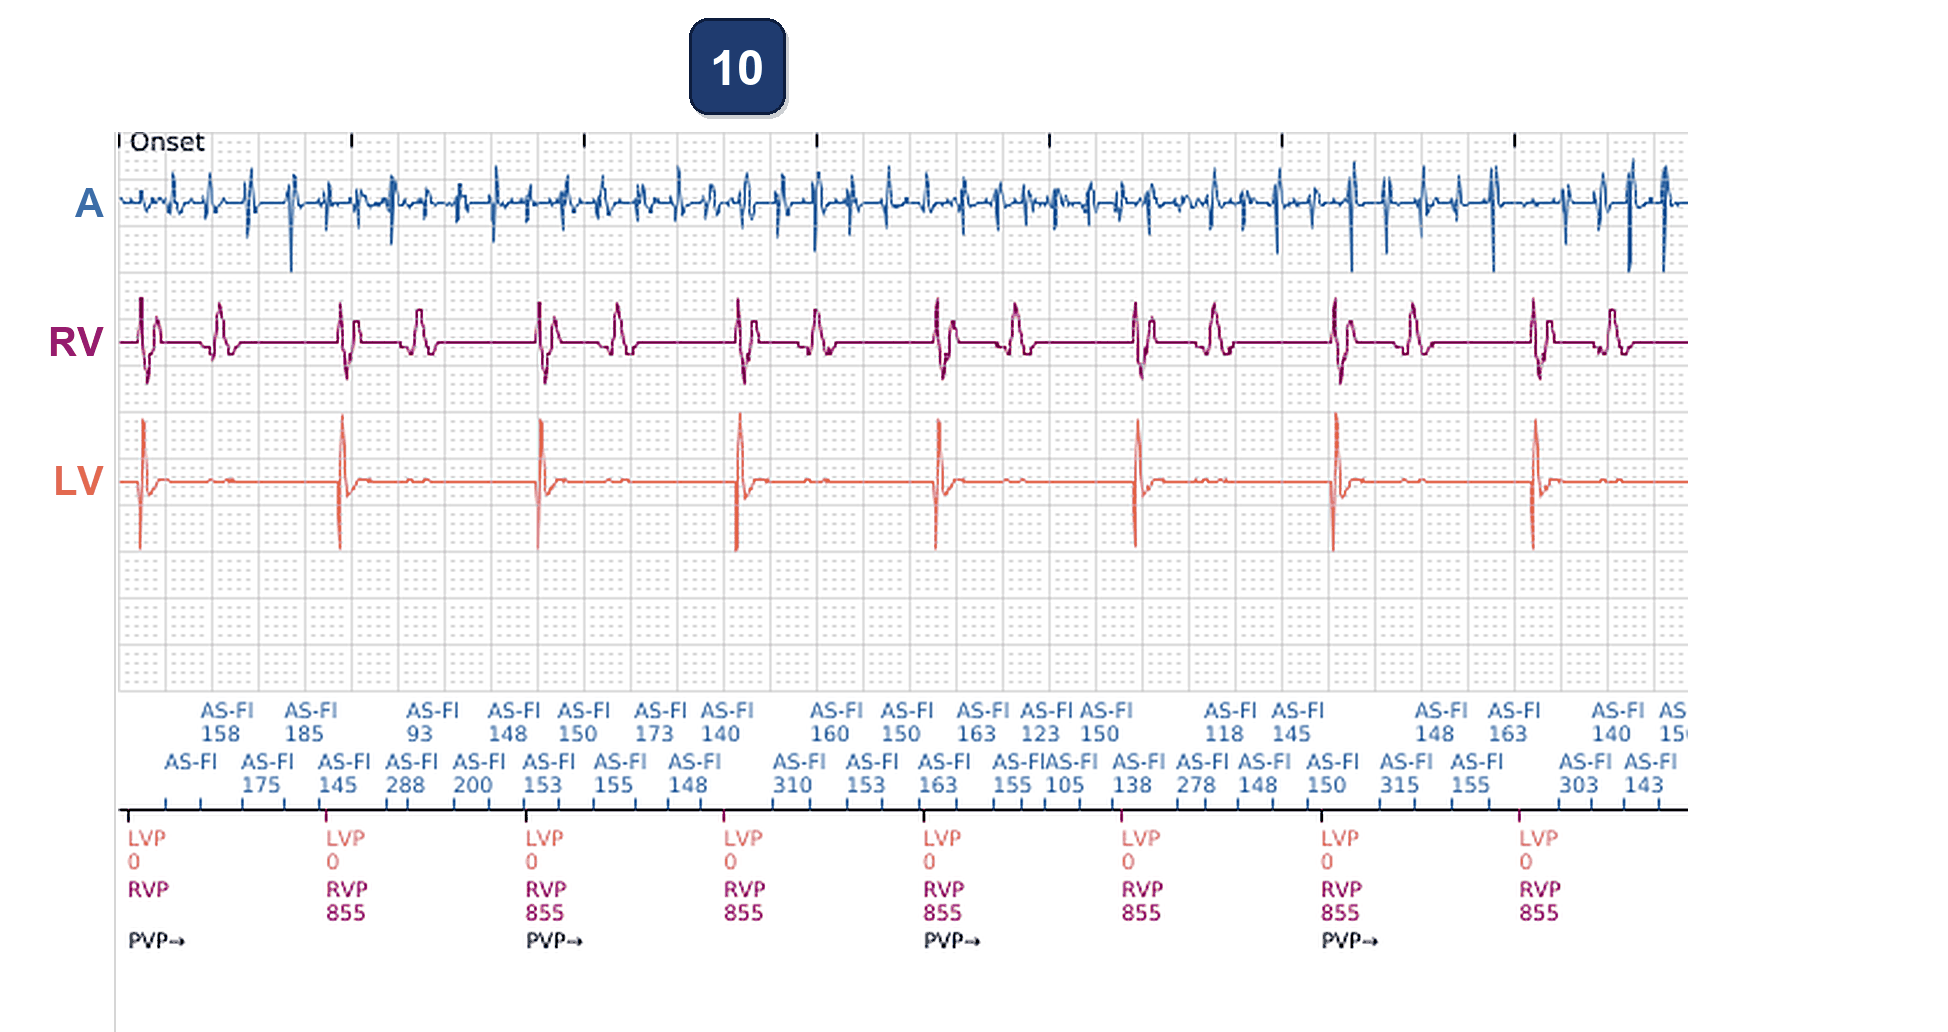
- The EGM of this report, still in AF, shows every beat BiV paced at 70 bpm (LVP 0 / RVP 855 ms): 100% BiV pacing
Points to remember
- In AF, split the beats in three: VRR beats (RVP-VR, LVP-VR) are true BiV beats; triggered beats (RVP-Tr, LVP-Tr) and sensed beats (RVS, LVS) are missed beats. Paradoxically a triggered beat holds no real RV pacing: the conducted beat is sensed in the RV, and that sense triggers the LV pace
- So in AF the % of RV pacing is the true % of CRT (here 32%): only the VRR beats are RV paced. The LV % (60%) is higher because it also counts the triggered LV paces
- Read the daily % pacing trend: the cumulative counters (99% since implant) hide a recent drop
- BiV Trigger and VRR cannot make up for fast conducted AF: here VRR paced only about a third of the beats. The fix is to control the conducted AF: here bisoprolol, then His bundle (AV junction) ablation, after which every beat was BiV paced, even in AF

Summary
- Fast conducted AF: only the VRR beats are true BiV beats; triggered beats (RV sensed, LV paced) and sensed beats are missed beats, so the RV % (32%) is the true % of CRT and the LV % (60%) overstates it. After His bundle ablation, every beat was BiV paced
Clinical pearl
Conducted AF with a drop in CRT warrants fast clinical action, to avoid a hospitalization for heart failure caused by tachycardia-induced and asynchrony-induced cardiomyopathy combined. Beta-blockers, or other antiarrhythmic drugs, can be a good first step. Some patients are candidates for AF ablation; others are good candidates for His (AV node) ablation, which is 99% effective in fixing this problem
Practice out loud
Just describe the tracing. What do you think is going on? Describing the numbers can help.
—
From Boston Scientific CRT — clinical cases by M. Strik. Published by Cardiocases. Every numbered marker on a recording is explained in the list beneath it; tap a marker on the trace or an entry in the list.