
Chapter 3 · Discrimination · Case 7
Bitachycardia ?
Patient
- A 72-year-old man with a triple-chamber defibrillator for dilated heart disease with healthy coronary arteries, an ejection fraction of 28%, complete left bundle branch block, and optimal medical therapy. The patient has never experienced a VT until now, and is known with paroxysmal AF. The patient consults due to a loss of consciousness the day before.
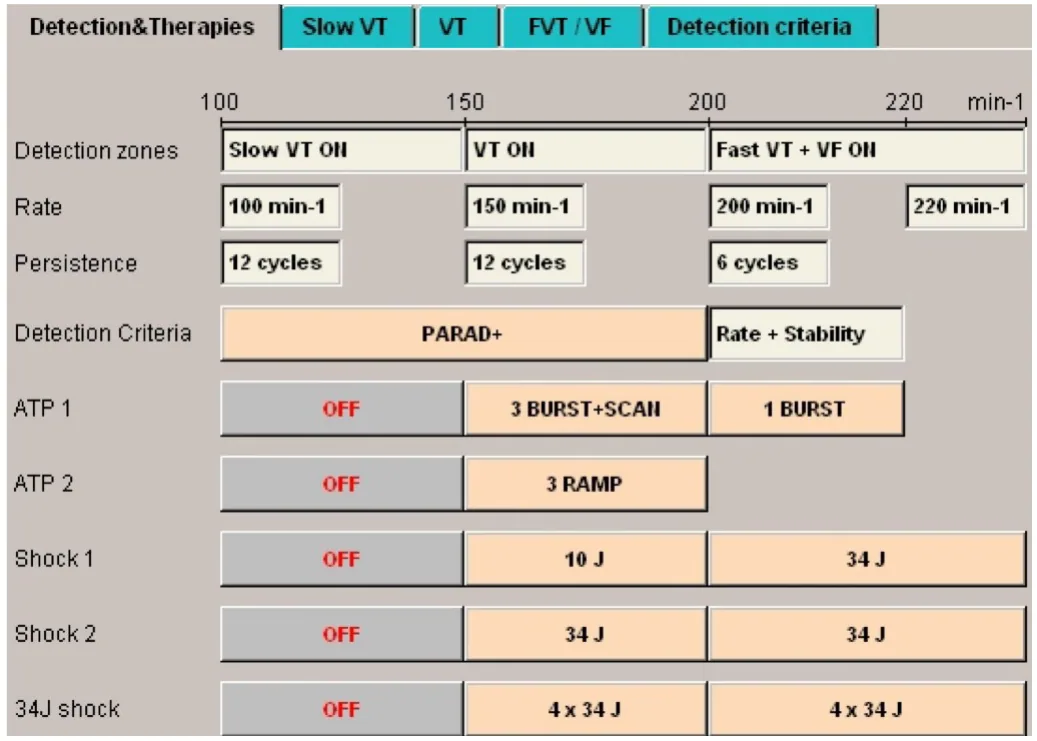
Programming
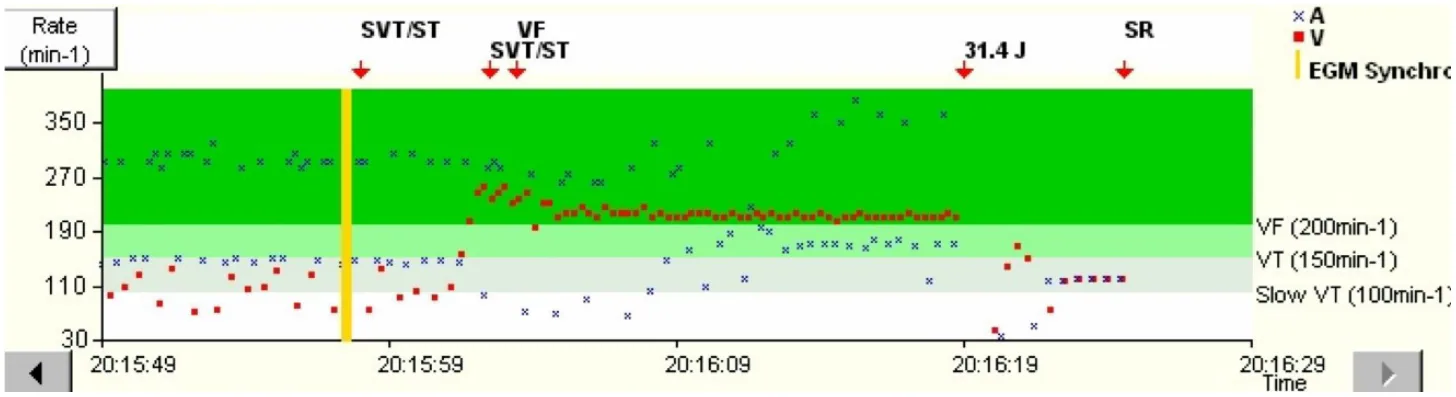
Interval plot
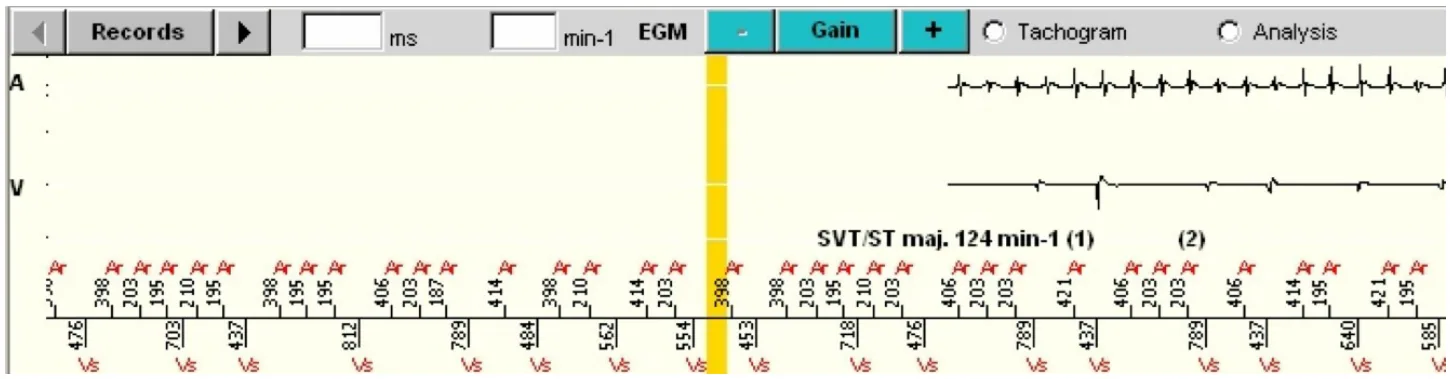
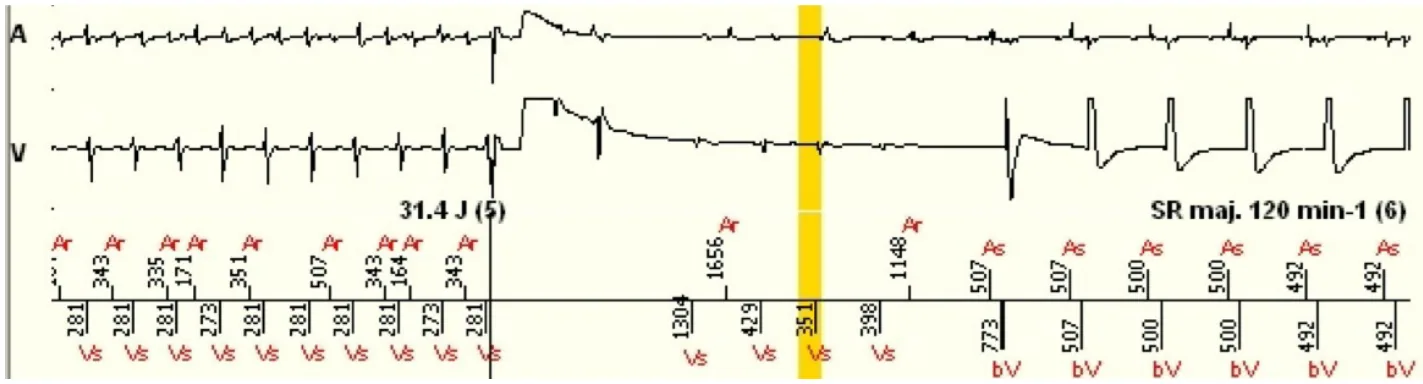
EGM
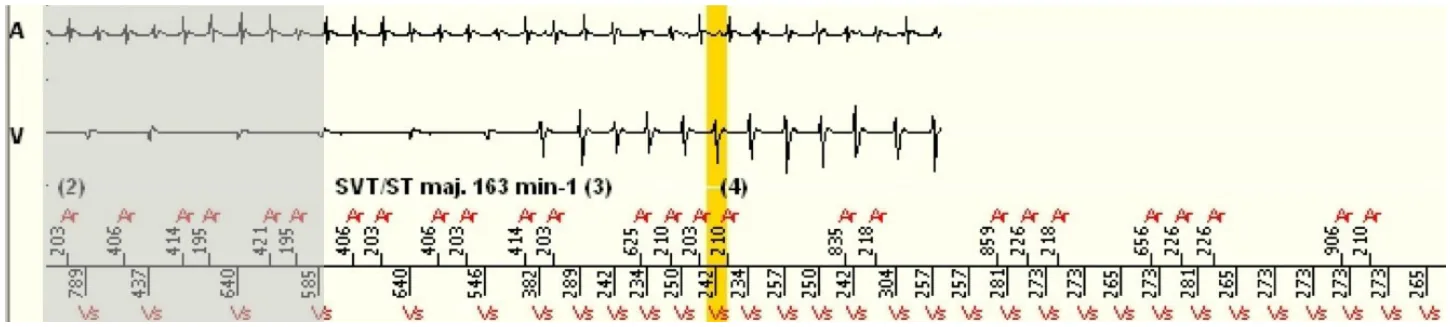
The shaded areas are the portions of the EGM that are the repetitions of the end of the previous image.
Your turn
What is your opinion?
- There is ventriculo-atrial crosstalk at the beginning of the tracing
- There is an atrial tachycardia at the beginning of the tracing
- There are detection errors during the atrial tachycardia
- The VF is relatively stable and a Fast ATP burst should have been triggered
- The device works perfectly
Interpretation
- The patient presents a sustained atrial rhythm disorder with variable conduction to the ventricle with cycles oscillating between the Slow and VT zones, such that a SVT diagnosis is proposed, and appropriate. Not all atrial cycles are visible since those in the post-ventricular atrial blanking are not detected.
- A tachycardia begins in the VF zone at 248 per minute, triggering an effective 31.4 Joule shock. This is a ventricular tachycardia and not a ventricular fibrillation given that the cycles tend to slow down over time (about 280ms at the time of the shock).
- Following 6 slow cycles out of 8, the episode is terminated.
- The atrial tachycardia has disappeared, the rhythm is associated. The shock terminated both the atrial tachycardia and VT simultaneously.
Comments
- The episode begins since 6 out of 8 cycles are in the Slow VT zone, although the rhythm is unstable and the tachycardia is classified as SVT.
- When the tachycardia begins and enters in the VF zone, no discrimination criterion is applied. Only the rate criterion will induce a VF-type therapy.
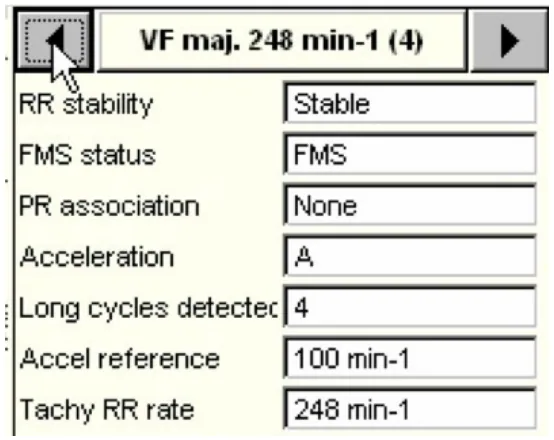
- At annotation (4), the diagnosis of VF is made and the programmed persistence of 6 cycles is initiated.
- Since the ventricular arrhythmia is 248 per minute when the persistence is reached, it is a shock that is directly issued and not an ATP burst for Fast VT which would only be applied if the rate had been between 200 and 220 per minute with strict stability as programmed. However, the EGM shows that the VT stabilises with regular cycles at about 280ms at the time of the shock. If the Fast VT zone had been set to 255bpm with a persistence of 20 cycles as recommended in primary prevention, an ATP could have been initiated (the rhythm has indeed become stable at the 20th cycle), with a good likelihood of termination.
- At the end of the persistence, the charging of the capacitors, although not noted by this former platform of the brand, begins.
- After a 1-second post-shock blanking during which two premature contractions occur that are not detected, the 4 ventricular events which are also premature contractions remain in the tachycardia zones. It takes the 6 associated As-BiV cycles to complete the episode (6 ventricular paced cycles).
- There is simultaneous termination of the atrial tachycardia and the VT. This situation represents a danger in a patient who is not being treated with an anticoagulant, and also represents a contraindication for the induction/termination of a VF with a test shock.
Take-home messages
No discrimination when the tachycardia is in the VF zone (Fast VT zone included). The stability criterion in the Fast VT zone is only used to decide whether or not to deliver an ATP before the charging of the capacitors.
Inducing and terminating a VF with a shock test in a non-anticoagulated AF patient is contraindicated if the absence of intracardiac thrombosis is not verified, and a flash anticoagulation has not been administered.
Practice out loud
Just describe the tracing. What do you think is going on? Describing the numbers can help.
—
From Implantable Cardioverter Defibrillator — Clinical cases from patients with MicroPort™ ICDs by M. Strik, A. Thiyagarajah, S. Ploux, P. Bordachar, P. Ritter. Published by Cardiocases. Each case is a question on real device interrogations: pick your answer, check it, then read the authors’ interpretation. Tap any figure to open it full screen.