
Chapter 1 · Counters · Case 4
Persistence
Patient
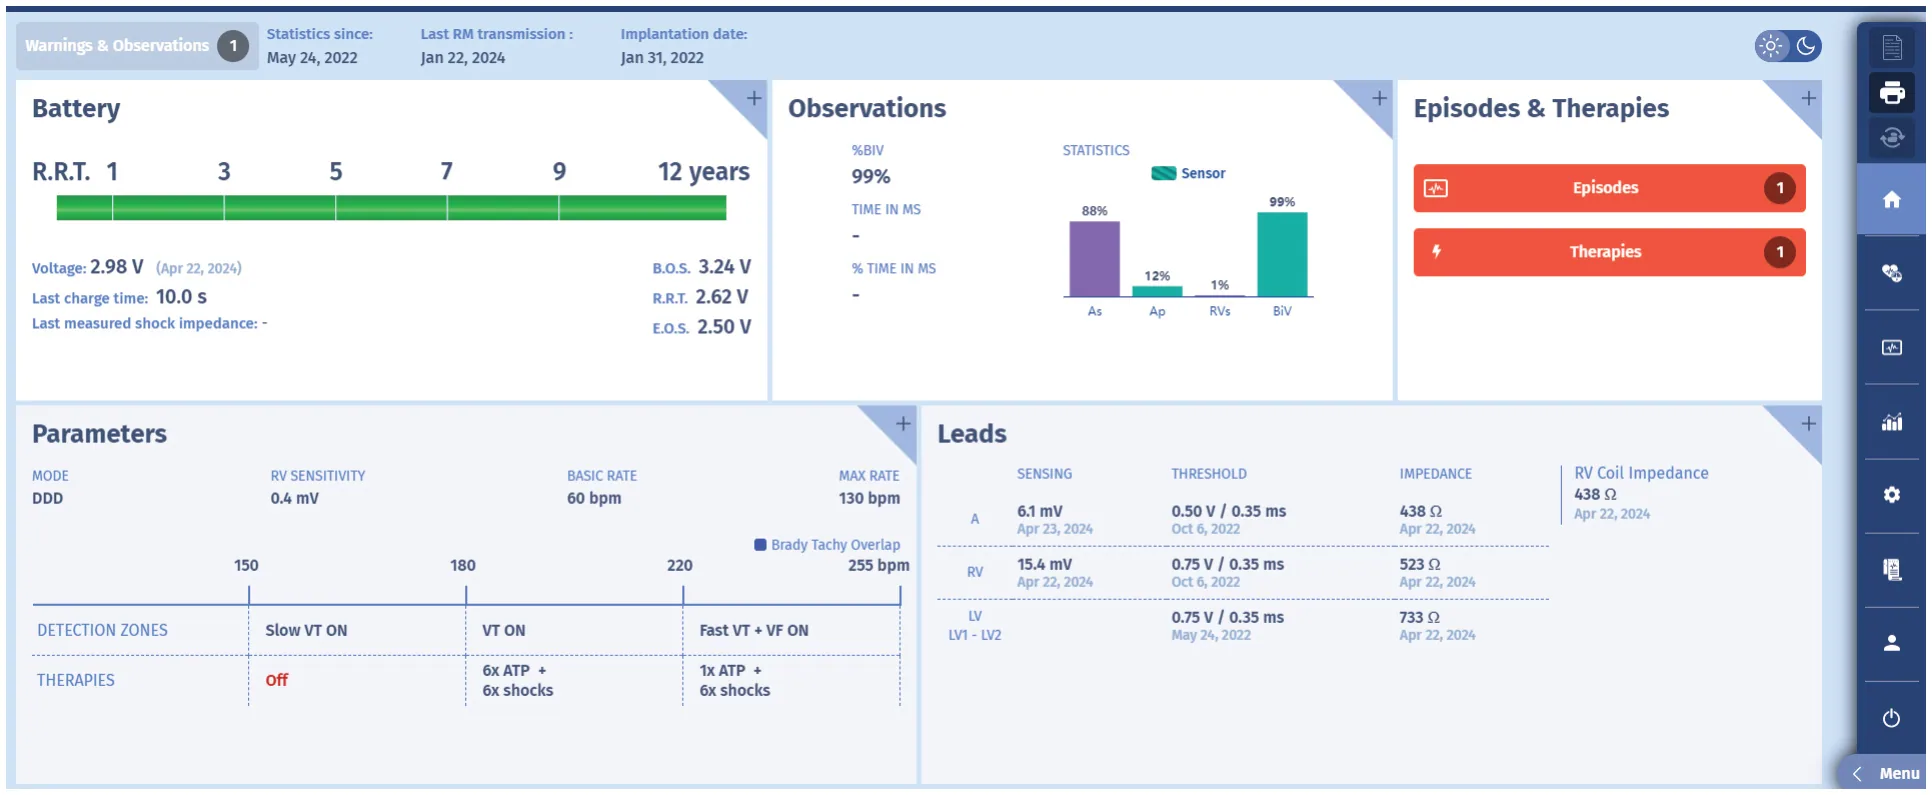
- 62-year old patient with dilated cardiomyopathy with left bundle branch block and reduced LV ejection fraction, implanted with a Gali CRT-D, comes for a check-up after an episode of palpitations.
Overview sceen
Your turn
Which of the following statements are correct?
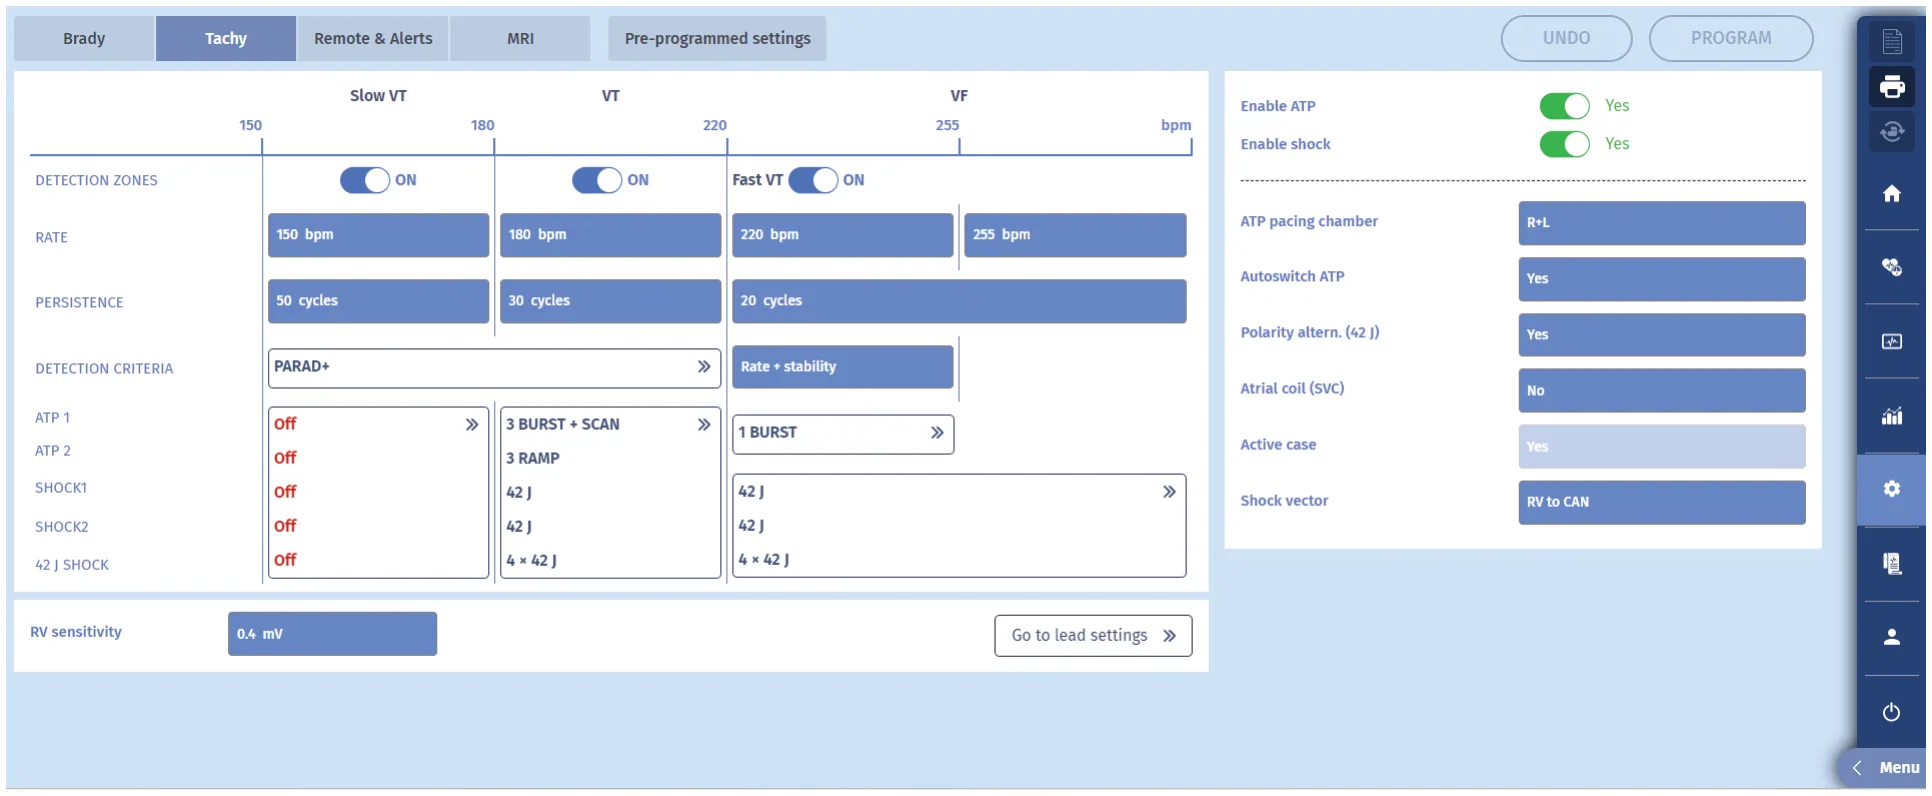
- The persistence in the VT zone is programmed at 30 cycles
- The persistence in the VF zone is programmed at 30 cycles
- The persistence in the VT zone is programmed at 20 cycles
- The persistence in the VF zone is programmed at 20 cycles
Interpretation
The programmer screen shows well functioning leads and a single episode which received therapy.
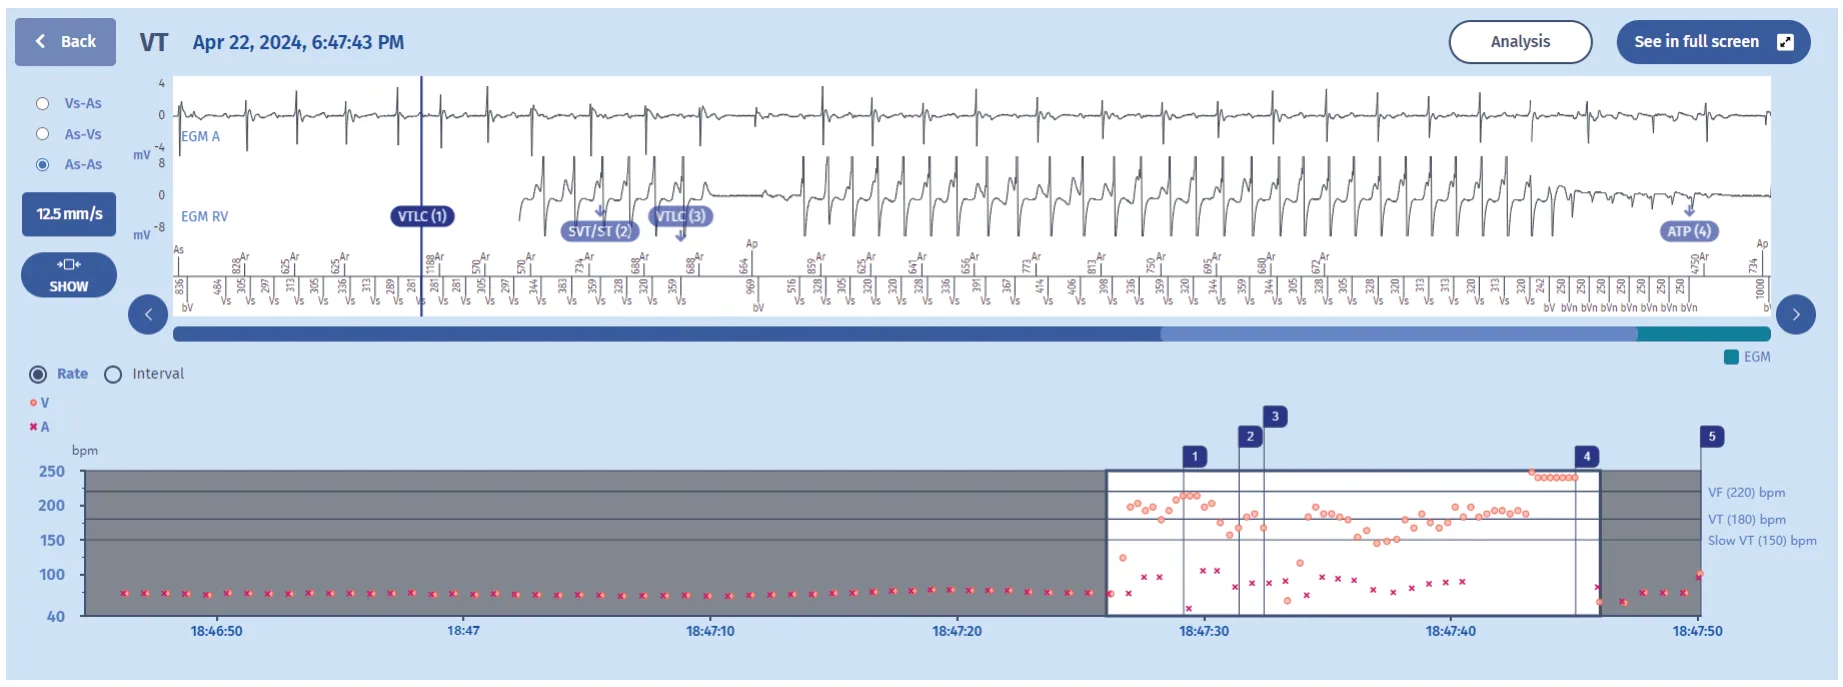
This is the episode:
Tachogram
After an slow and regular rhythm suggesting atrial sensing and biventricular pacing, there is a sudden acceleration of ventricular cycles. As there are more ventricular events than atrial events, the episode is highly suspicious of ventricular tachycardia, in the VT zone. Marker 1-3 are related to counters and marker 4 is an ATP, which is succesful.
EGM
- The rate of the initial rhythm around 70 beats per minute
- Then the diagnosis of VT (Marker 1: VTLC) is made after 6 out of 8 cycles in the VT zone.
- The rhythm becomes irregular, the ICD suspects atrial fibrillation and so displays the second marker: SVT/ST
- After a few more cycles, the rhythm again stabilises and the third marker shows: VT
- When the persistence counter is completed (more details about this later), an ATP is delivered (burst with 8 pulses) which terminates the VT
- After 6/8 slow events, marker 5 marks the end of the episode
Comments
The persistence counter is essential for two reasons.
- It prevents unnecessary therapy by allowing nonsustained ventricular arrhythmias to self terminate. Multiple studies have shown that therapy of ventricular tachycardias by shocks is deleterious for the patient. Shock may be delivered because ATPs are not successful but also because ATP may even accelerate the arrhythmia into the VF zone. All efforts need to be made to avoid ICDs treating VT and programming a long persistence is probably the most efficient method. In the VT zone the persistence should be programmed at 20 or 30 but it can even programmed to 200.
- It prevents inappropriate therapy by allowing for supraventricular arrhythmia or noise to self terminate before the wrong diagnosis (VT or VF) is made. Noise is often expressed as short bursts of ventricular oversensing and programming a persistence of 20 cycles or more is very efficient in preventing the filling of the persistence counter during bursts of noise. Supraventricular arrhythmias can be errounously diagnosed as VT for many reasons and a longer persistence counter gives the ICD more chance to rediagnose the arrhythmia as supraventricular. In MicroPort ICDs, the discrimination algorithms work continuously, also during the persistence, which is why long persistence counters greatly reduce inappropriate therapies in case of supraventricular arrhythmias.
The menu showing the possible options for persistence in the VT zone:

Here is a figure going in depth of the working of the persistence counter in this case:
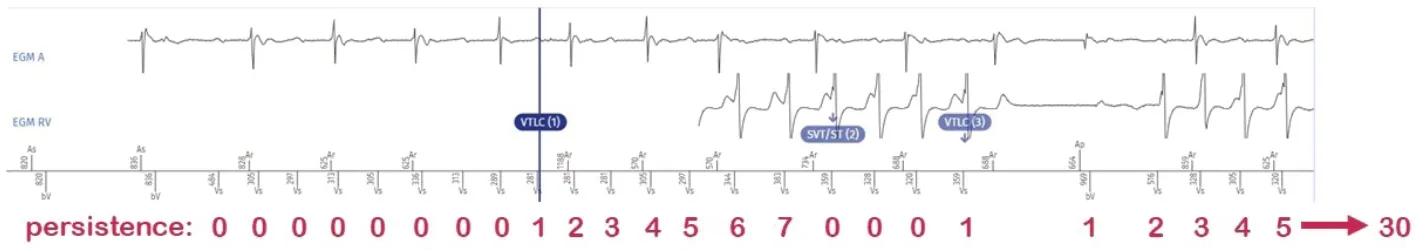
The persistence counter starts every time when the VT/VF majority is filled and starts at a value of 1. As we can see in this figure, the persistence counter is reset to 0 when the diagnosis is no longer VT (but SVT/ST in thise case). The persistence counter restarts at 1 when the diagnosis of VT (VTLC 3) is again made. Interestingly, there is a short interruption of the VT. While the VT majority remains filled (meeting the 6/8 criterium), the persistence counter is frozen (+0) until there are new events in the VT zone (+1). In this case, the persistence counter needed to reach 30 before the first therapy is launched (ATP in this case).
Take-home message
Persistence counters are essential in MicroPort ICDs as they significantly decrease the amount of unnecessary and inapropriate therapies. One of the most important reasons why we see a lot less therapies the last decade, is due to the systematic programming of longer persistence counters than in the past.
Practice out loud
Just describe the tracing. What do you think is going on? Describing the numbers can help.
—
From Implantable Cardioverter Defibrillator — Clinical cases from patients with MicroPort™ ICDs by M. Strik, A. Thiyagarajah, S. Ploux, P. Bordachar, P. Ritter. Published by Cardiocases. Each case is a question on real device interrogations: pick your answer, check it, then read the authors’ interpretation. Tap any figure to open it full screen.